

It begins simply enough: the blood draw for the obligatory annual physical. The typical program is to conduct all tests known to medicine, or at least it seems that way — a series of three-letter acronyms that produce a Byzantine array of numbers. About 30 years ago, they added a test for guys (women have their own gender-specific tests): the PSA, short for prostate-specific antigen. A rather handy test, like several of the others, this is a warning bell of sorts that further investigation is needed. The reference range on the IU Health Lab results page is 0 to 4, with anything above 2 flagged as “High.” Mine had been climbing for a while. This draw was 5.44.
So, armed with an elevated PSA, I went in to see the primary care doctor, who performed the dreaded digital rectal examination. (Current best practice is that this test is no longer routinely recommended, but most patients aren’t well-positioned to argue in the moment.)
“It’s enlarged,” the doctor helpfully reported.

Next stop: the urologist’s office. After a review of the data, another digital rectal exam (this one is recommended), and off to the imaging folks for a dye-contrast MRI. Everyone over 45 has had a colonoscopy, so no big deal prep here: “Give yourself a saline enema and wait for it to work.” An hour or so after nature takes its course, they hang an IV with a magic dye, then the banging, clicking and whirring of the MRI machine becomes a cadence. A few days later, the next visit with the urologist brings the “What’s next?” conversation. As with a lot of modern medicine, a lot. The MRI shows “an area of interest,” as though this were part of the Grand Canyon tour.
Next was a biopsy. The prep for the transrectal biopsy is a lot like the MRI: a mini-enema. For the procedure itself, you lie on your side after they swab the area with a Betadine disinfectant, and the doctor inserts a golf ball-sized probe. The probe is an ultrasound head with a hole in it to allow the insertion of needles and a spring-loaded core gun. The initial injection and the first few core extractions sting a bit, but this is more a nuisance than anything else. Fifteen minutes later, it’s all over.
A few days later comes the pathology report. This report shows where the “thing of interest” was found and what the results were from the analysis of the 10 core samples. The report helpfully distinguishes the positive samples with the word MALIGNANT in bold red lettering, as though you might not review all 10 results. The other morsel here is a mysterious number: the Gleason score. The Gleason score was invented by Donald Floyd Gleason, an American physician and pathologist. He developed the prostate cancer grading system in the 1960s while working at the Minneapolis Veterans Affairs Medical Center.
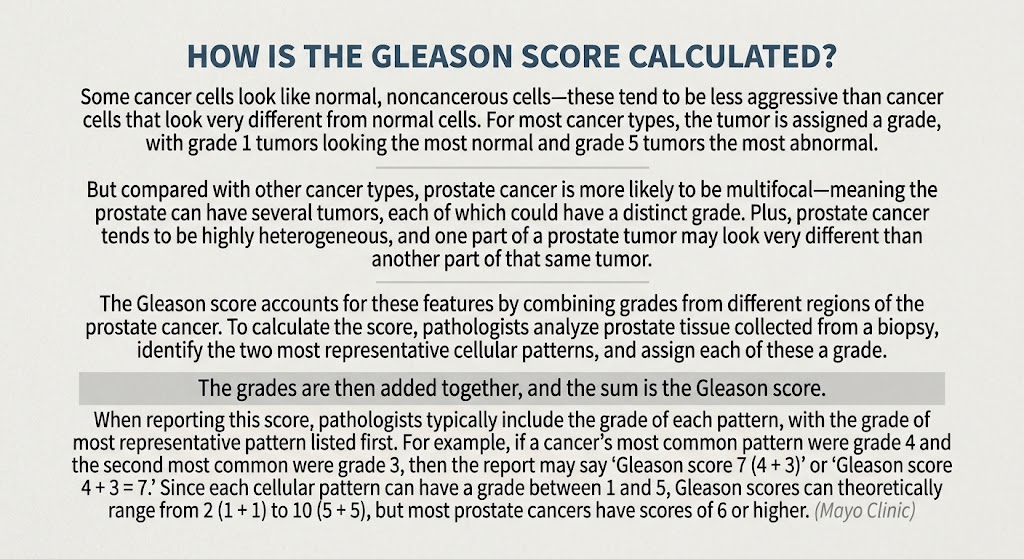
Now, this report arrives long before the visit with the urologist, who helpfully explained that all men, sooner or later, have prostate issues. Read that again. He went on to explain that for low Gleason score cancers, they actively monitor. This is urology-speak for increased PSA testing and more biopsies. Some urologists don’t even think it should be called cancer.
One might hope that this would be the happy ending of this not-so-Hallmark story. Not so. Fast-forward to the next annual physical, where the already elevated PSA jumped another 5 points. Cue panic. It seems the annoying little gland can hold multiple tumors of different types of cancer.
Back to the urologist, where there is a discussion about another biopsy. No problem, I thought, had that before. This go-round was transperineal, or under the scrotum. “You’ll be asleep, nothing to worry about.” The upside was no bowel preparation and front-side sampling, where the tumor we knew about was located. The surgery center was freezing; despite warmed blankets and my wife’s coat, I longed for a parka. After waking up from the general anesthesia, my handlers chauffeured me home and tucked me in to sleep off the rest.
That Friday before Memorial Day came the news about the newest biopsy: 23 samples, three malignant. Ah, no big deal, same result as before. However, it wasn’t.
“They want to see if your tumor has a friend,” said my daughter, who is a doctor.
It did. The friend was sketchy.
The new Gleason score was higher, and the front number was “of concern,” which is urology-speak for time for action. A day after Memorial Day, I was in the PET scanner for a fun-filled scan of radioactive markers suspended in sugar water. It seems cancer likes sugar. The PET scan lit up like a Christmas tree.
Welcome to “Let’s Make a Clinical Deal.” I could see Monty Hall standing in front of a series of doors. (It’s amazing the things a frightened brain does while awake in the middle of the night.)
Door No. 1: Robot-assisted radical prostatectomy. This surgery is performed by the surgical team and a $2.5 million robot the size of a small car. Fascinating and horrifying all at once. (Cue all the alien-abduction sci-fi images.)
Door No. 2: Radiation oncology. Broad-beam radiation, administered over about a month, literally cooks the tumors. The good news is that it is very effective, tends not to cause incontinence, and preserves sexual function. There are, however, downsides — not least being that it leaves large swaths of scar tissue that can make surgery more difficult if necessary later. The other challenge is that these days, anti-hormone treatments are administered to lower testosterone to zero. These treatments last a year and have predictably unpleasant side effects.
Door No. 3: Other treatments. Several clinics are testing electric ablation (sort of like targeted microwaves), and others are using freezing to kill the tumors.

After a couple of consultations with radiation oncologists, regular oncologists, another urologist and my daughter, it was time to exert some control over this mess. I called to schedule surgery.
The first proposed date was my birthday. “Oh, no, that won’t work…”
We selected Bastille Day, July 14. The Bastille was a prison and military facility in Paris. French peasants stormed it on July 14, 1789, starting the French Revolution. It remains, very much like our Independence Day, a day of celebration. I thought it was a perfect metaphor.
So, the planning for how to keep all the plates spinning began. The sit-ups and crunches began that day, too. “They want you to have six-pack abs,” my daughter helpfully extolled. I am not sure I ever had three-pack abs, let alone six-pack.
Bastille Day arrived. The surgery lasted about three hours, and when I woke up in recovery, the weight of worry was gone. Post-op, they give you new toys: a Foley catheter and an incentive spirometer among them. There was also a very snug girdle to keep everything “where it belongs.” I learned a lot that day, and more overnight. There were veiled references to bladder spasms triggered by caffeine and alcohol. Don’t have either, I was warned. The spasm lasted about 15 minutes. I understood labor from childbirth for the first time.
Ten days post-op, you report to the X-ray folks. They push dye into your bladder and start taking X-rays, the object being to see the healing of the urethra.
A short time later, the surgeon blessed these images, but only after a book-club-worthy discussion (10 minutes’ worth!) with my wife and daughter about a new book. The physician assistant had read it. Far be it from me to interrupt this intellectual exchange.
“Don’t worry, we’ll talk about you in a minute,” I was assured by the surgeon.
Eventually, I was inspected and blessed. The catheter was removed. (It didn’t hurt.) I was freed, but only after a lengthy soliloquy about not overdoing it, as though I were going to rush out to run a marathon.
Cancer support experts tell you to lean on your network. “You’ll need all the support you can get,” reports the American Cancer Society. They were right, of course. I chose not to keep this a secret. (I’m having “I waive my HIPAA rights” T-shirts printed.)
Sometime before surgery, I had been congratulated by a friend for “being pregnant.” I explained that she had been fed fake news: “I have prostate cancer.”
“Oh, I know that. Doesn’t change the fact that you’re pregnant. You will wet your pants every time you laugh, cough or sneeze; you’ll know where every bathroom is in the region; and you won’t be able to lift anything heavier than a carton of milk. You’re ‘pregnant,’ so start doing your Kegel exercises, buttercup!”
She wasn’t wrong.
There is another second-order effect of removing the prostate gland. Even with a nerve-sparing technique, the trauma to the various tissues creates erectile dysfunction (ED). This improves over time, but it takes patience. The urology folks have many tricks in their bag, some better than others. But resolving this part can take up to a year. Seems a small price to pay.
So now, a few weeks post-op, incontinence is better, sleep is better, appetite is returning, and ED is hanging around. (I can’t get into the bathtub because of the incision sites, so I’m not sure how the Cialis will work out.) I am 20 pounds lighter (still don’t have abs), and my ambitions to be a swimsuit model are dashed, but I am here and will be for a long while.
The moral of the story: Go get a PSA test, fellas.
Guest Contributor Peter Beering
Peter Beering, Esq., is an internationally recognized expert in emergency preparedness, planning, response, counterterrorism, arson, bombings and coffee. He is a resident of Carmel, Indiana.



